
Understanding your shoulder
Shoulder replacement
A plain-language guide to why a shoulder is replaced, the types of replacement, what the operation involves and what recovery looks like.
Prepared by Mr Phil Wright, consultant shoulder and elbow surgeon. For educational purposes only.
The short version
Shoulder replacement is an operation for a painful, worn shoulder joint that no longer responds to simpler treatment. Its most reliable benefit is pain relief; movement usually improves too, though not always to normal. About nine in ten replacements are still in place ten years later. Recovery takes months, not weeks, and the exercises matter as much as the operation.
Why a shoulder is replaced
The shoulder is a ball and socket joint. The ball is the top of the upper arm bone (humerus) and the socket (glenoid) is part of the shoulder blade. Both are lined with smooth cartilage. When that lining wears away, bone rubs on bone and the joint becomes painful and stiff.
The common reasons are:
- Osteoarthritis, the gradual wearing out of the joint surface.
- Cuff tear arthropathy, arthritis that develops after a large, long-standing rotator cuff tear.
- Inflammatory arthritis, such as rheumatoid arthritis.
- Fractures of the top of the humerus, or their later consequences.
When it is worth considering
A replacement is not a first step. It is considered when pain, particularly pain at night, and loss of everyday function persist despite painkillers, exercise or physiotherapy and, in some people, a steroid injection. X-rays, and sometimes a CT or MRI scan, are used to confirm the extent of the arthritis and to check the bone and the rotator cuff tendons.
The decision is yours. Arthritis of the shoulder is not dangerous, so the question is whether the symptoms are bad enough to justify an operation and its recovery.
The types of replacement
| Type | What it is and when it suits |
|---|---|
| Anatomic total replacement | A metal ball on the humerus and a plastic liner in the socket, in the normal arrangement. It relies on a working rotator cuff, so it suits arthritis with intact tendons. |
| Reverse total replacement | The arrangement is swapped: a ball is fixed to the socket side and a cup to the humerus. The large deltoid muscle then lifts the arm in place of the rotator cuff. It is used when the cuff is torn or weak, when the socket is badly worn, for some fractures, and increasingly for arthritis in older patients. |
| Partial replacement | Only the ball is replaced. This is used much less often than it once was. |
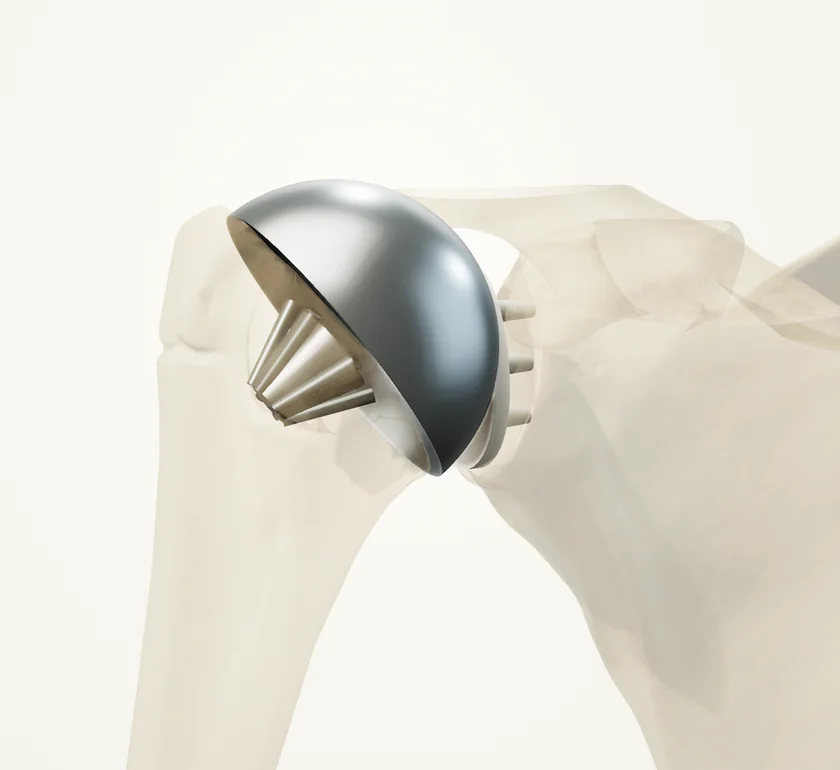
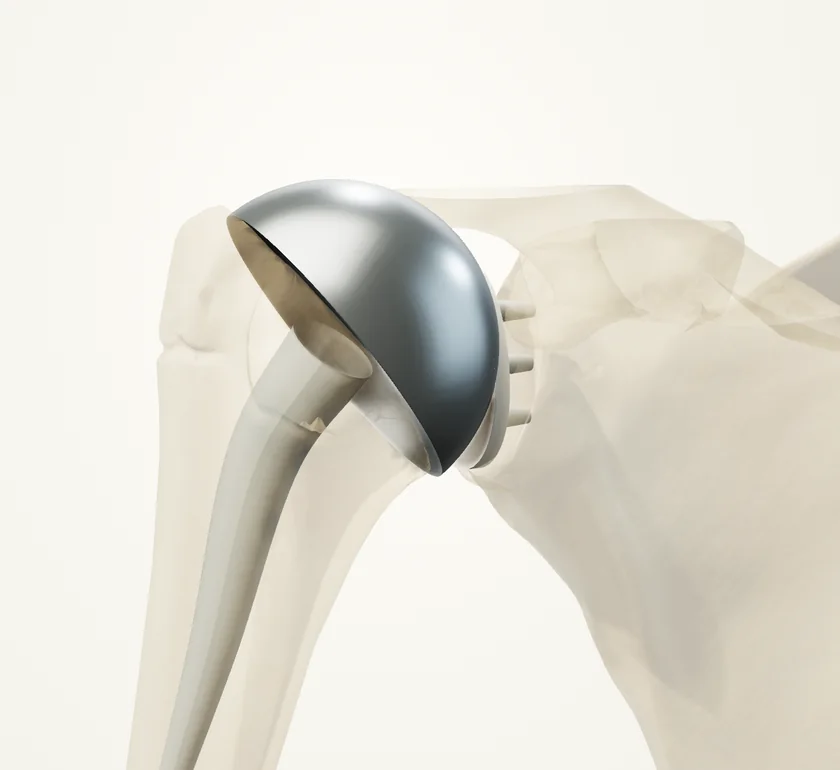
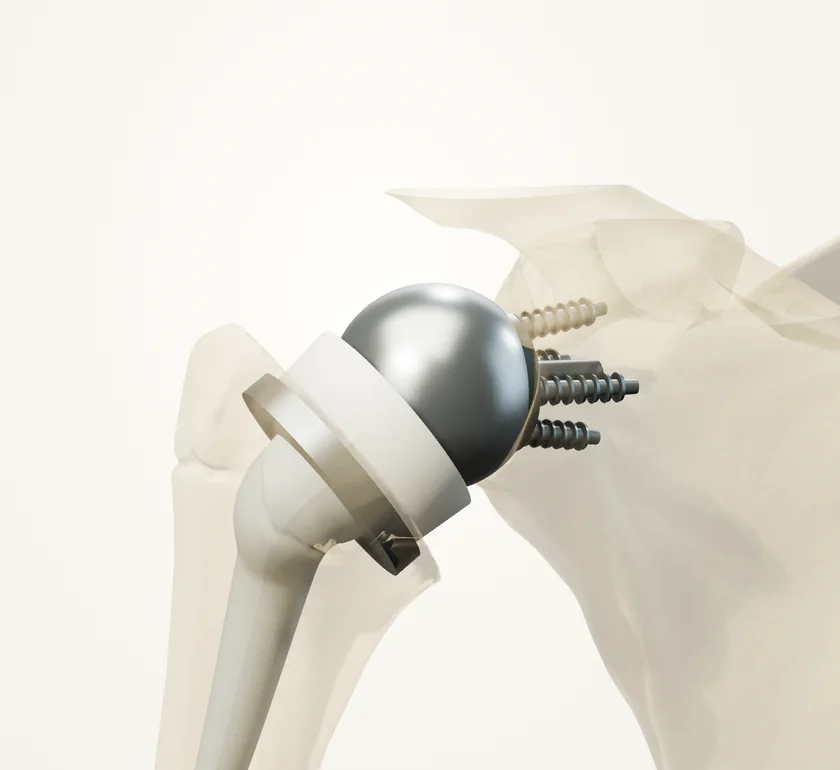
Right shoulder seen from the front, with the bone drawn see-through to show how each implant is fixed. In the reverse design the ball is fixed to the shoulder blade with a plate and screws, and sits in a plastic-lined cup on top of the stem. These are illustrations, not specific implant designs.
Stemmed or stemless
In an anatomic replacement the ball has traditionally been mounted on a stem that runs down inside the humerus. Where the bone is strong enough, it can instead be fixed by a short anchor in the top of the bone, with no stem. This is a stemless replacement. It preserves more of your own bone, and in randomised trials movement, function and the need for further surgery were no different from a stemmed implant over the first few years, although long-term results are still being gathered.1 It is Mr Wright's preferred design for an anatomic replacement where the bone allows. Bone quality can only be judged for certain during the operation, so a stem is occasionally used instead.
Which type suits you depends on your tendons, the shape of your bone, your age and what you need the arm to do. Mr Wright will explain the reasoning in your case. You can see each design on the 3D shoulder model under "Surgical procedures".
What you can expect from it
Most people get a large and lasting improvement in pain. Movement and strength usually improve, but a replaced shoulder rarely moves like a normal one, and reaching behind the back is often the last movement to return, particularly after a reverse replacement.
Pooled studies with at least ten years of follow-up found that about nine in ten shoulder replacements were still in place at ten years, with benefit to pain and function lasting over that time.2 In the UK National Joint Registry, around 4 in every 100 planned shoulder replacements have needed a further operation (revision) by five years. The risk is higher in younger patients, who place greater demands on the joint for longer.3
The operation
- It is usually done under general anaesthetic, often with a nerve block that numbs the arm for several hours afterwards.
- The incision is at the front of the shoulder and the operation takes one to two hours.
- Most people stay in hospital for one or two nights.
- You will wake with your arm in a sling and begin gentle exercises before you go home.
Risks
Most people have no serious complication, but no operation is free of risk. The figures below are averages from large studies. They are a guide, not a prediction for you: your own risk depends on your age, your general health and the type of replacement, and is discussed with you before you decide.
Problems with the shoulder itself
Taking all of them together, published series report a complication of some kind in roughly 10 to 16 in every 100 shoulder replacements.4 Many of these are minor or settle without further surgery.
- Infection. Uncommon, but serious if it reaches the implant, when further surgery is usually needed.
- Dislocation or instability of the new joint. This is the most frequent complication after a reverse replacement.5
- Fracture of the bone around the implant, during or after surgery. After a reverse replacement this includes stress fractures of the shoulder blade.
- Nerve injury, causing numbness or weakness. This is usually temporary.
- Stiffness, or less movement than hoped for.
- Later failure of the rotator cuff, or loosening of the socket component, after an anatomic replacement. In one large series each affected about 3 in every 100.6
Further surgery
About 4 in every 100 replacements are revised within five years.3 Over a lifetime the chance depends strongly on age at the time of surgery: from about 1 in 37 for women aged 85 and over to about 1 in 4 for men in their late fifties.7
General medical complications
In a study of more than 58,000 shoulder replacements in England, about 1 in 22 people (4.6 in 100) had a serious medical problem within 90 days. The most frequent were chest infection (about 2 in 100), urinary infection (1 to 2 in 100) and kidney injury (1 in 100). A clot on the lung and heart attack each affected about 3 in 1,000. These risks rise with age and with other medical conditions.7
Recovery
The timings below are typical. Yours may differ according to the type of replacement and how the operation went, and you will be given a plan to follow.
| When | What to expect |
|---|---|
| First 4 to 6 weeks | Sling, worn day and night at first. Hand, wrist and elbow exercises, and gentle assisted shoulder movement as shown by your physiotherapist. No lifting. |
| 6 to 12 weeks | Sling discarded. Moving the arm under its own power, gradually increasing range. Light everyday use at waist height. |
| 3 to 6 months | Strengthening. Most everyday activities become comfortable. |
| Up to 12 months | Improvement continues, more slowly. |
Driving and work
Most people are ready to drive at around six to eight weeks, once out of the sling and able to control the car safely; check with your insurer. Desk work is often possible within a few weeks. Manual work takes three months or more, and heavy or repetitive overhead work may not be advisable in the long term.
Looking after the new joint
Swimming, walking, golf and similar activities are generally fine once you have recovered. Heavy lifting and contact sports put the implant at risk and are best avoided.
When to seek help
- increasing redness, swelling or discharge from the wound, or a fever
- sudden severe pain, or a sudden loss of movement in the shoulder
- new numbness or weakness in the arm or hand once the nerve block has worn off
Call 999 for chest pain or sudden breathlessness. A painful, swollen calf needs urgent same-day assessment.
Sources
- Outcomes between stemmed and stemless total shoulder arthroplasty: a systematic review and meta-analysis of randomized controlled trials. JAAOS Global Research & Reviews 2022. Full text.
- Evans JP, et al. How long does a shoulder replacement last? A systematic review and meta-analysis of case series and national registry reports with more than 10 years of follow-up. Lancet Rheumatology 2020;2:e539-48. Summarised by the National Institute for Health and Care Research.
- National Joint Registry annual report, shoulder section, as cited in O'Malley O, Davies A, Sharabani MTA, et al. Revision of reverse shoulder arthroplasty by indication: a National Joint Registry study. Bone & Joint Open.
- Bohsali KI, Wirth MA, Rockwood CA. Complications of total shoulder arthroplasty. Journal of Bone and Joint Surgery (Am) 2006;88:2279-92.
- Bohsali KI, Bois AJ, Wirth MA. Complications of shoulder arthroplasty. Journal of Bone and Joint Surgery (Am) 2017;99:256-69.
- Parada SA, Flurin PH, Wright TW, et al. Comparison of complication types and rates associated with anatomic and reverse total shoulder arthroplasty. Journal of Shoulder and Elbow Surgery 2021;30(4).
- Craig RS, Lane JCE, Carr AJ, Furniss D, Collins GS, Rees JL. Serious adverse events and lifetime risk of reoperation after elective shoulder replacement: population based cohort study using hospital episode statistics for England. BMJ 2019;364:l298.
- National Institute for Health and Care Excellence. Joint replacement (primary): hip, knee and shoulder. NICE guideline NG157, 2020.
This guide is for educational purposes only. It is not to be used in place of consultation with a medical professional, and it cannot take account of your own circumstances.